FHO+ rules
Indirect care vs clinical administration
Separate the two support categories that are easiest to confuse.
Quick answer: Indirect care is tied to a specific patient or patient encounter. Clinical administration is broader work for the roster or FHO patients that requires physician expertise. Ordinary clinic management is neither.
Last reviewed October 9, 2026
Use the patient-specific test
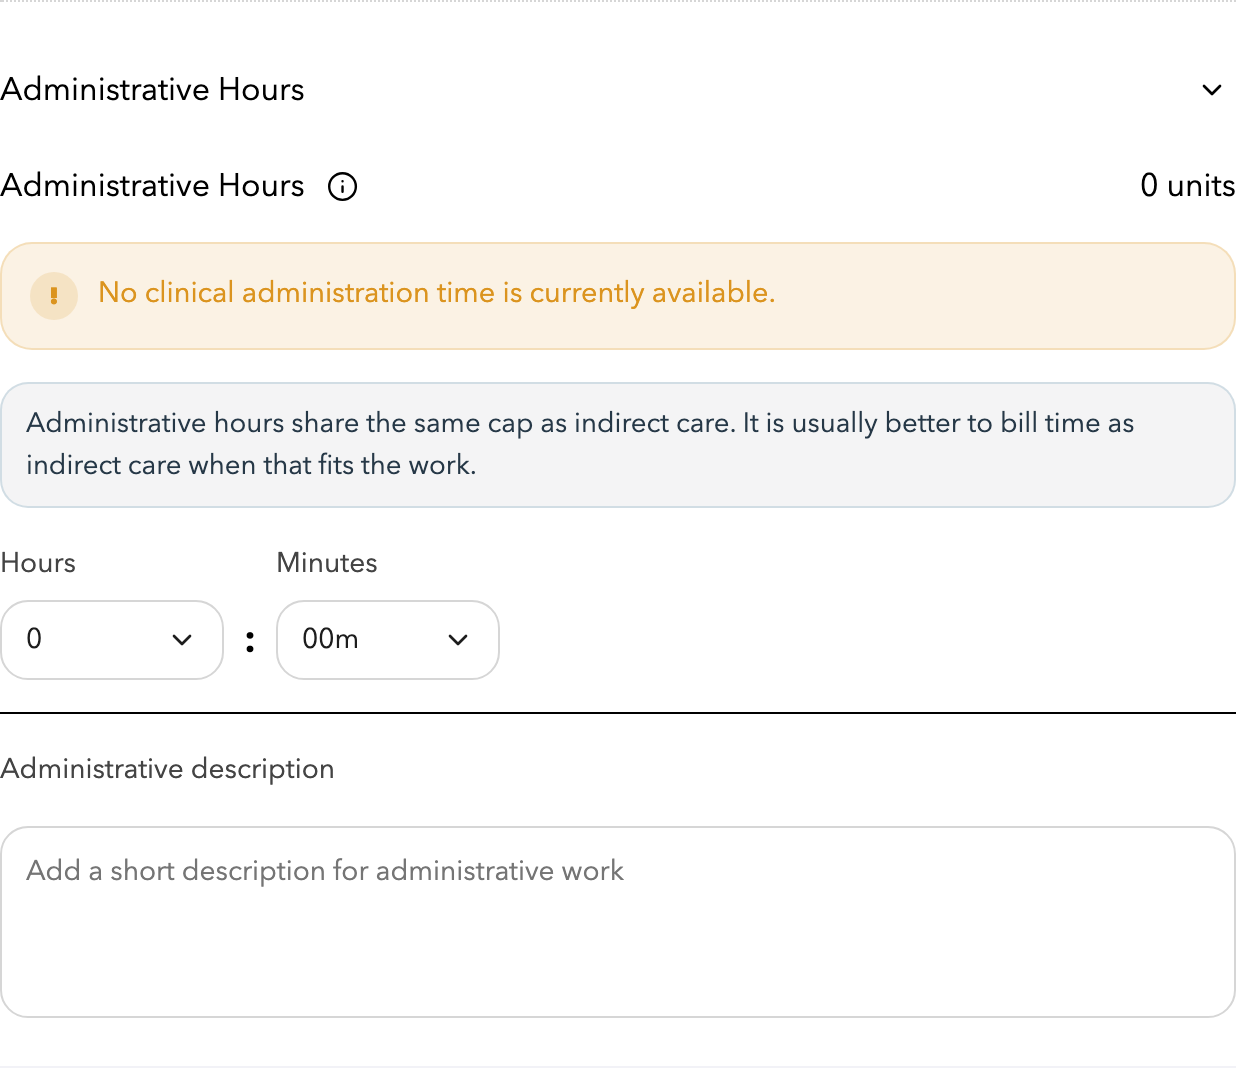
For many routine support tasks, Q312A is the right fit because the work is about an individual patient. Keep Administrative Hours closed unless you performed a distinct, eligible Q313A activity. Q312A and Q313A have the same base rate and share the combined support pool, but Q313A also has its own tighter monthly limit. The categories are not interchangeable.
- If you can identify the patient or encounter the work is about, review Q312A indirect care.
- If the work concerns a panel, program, or clinical system rather than one patient, review Q313A clinical administration.
- If the work is business or operations work that does not require physician clinical expertise, it does not belong in Q313A.
Q312A indirect patient care
- Charting and documenting patient interactions.
- Reviewing labs, imaging, consultation notes, and other patient reports.
- Preparing referrals and requisitions.
- Patient-specific care planning, coordination, conferencing, and clinically related communication.
- Clinically required patient forms and reports, excluding uninsured third-party requests.
- Patient-specific teaching that arises from direct patient care.
Q313A clinical administration
- Proactive roster management for screening, immunization, chronic disease, and similar care programs.
- EMR updating or management that requires physician expertise.
- Quality-improvement planning and clinic implementation related to care access, equity, or digital health.
Do not claim as clinical administration
- Employee management and human resources.
- Finance, accounting, insurance, leasing, and supply or equipment ordering.
- General infrastructure work that does not require physician clinical expertise.
- Time spent tallying, entering, or documenting FHO+ hourly claims.
Same base rate, different rules
Use the category that describes the work. Do not move time to Q312A because it feels simpler, or to Q313A because a different amount of room appears available. The OMA guide separates patient-specific work from roster-wide clinical administration.
| Category | Base rate | Monthly limit |
|---|---|---|
| Q312A indirect care | $80 per hour | Counts toward the combined 25% support pool. |
| Q313A clinical administration | $80 per hour | Counts toward the combined 25% support pool and a separate 5% of direct, telephone, and indirect hours. |
Important notes
- When one work block contains different tasks, record the actual time in the category that describes each task.